
Bioethical Issues: 25 Controversial Examples Explained
Bioethical issues are hard moral questions that come from biology, medicine, and health care. Should parents be allowed to edit their baby’s genes? Who gets the next donated kidney? Can a dying patient ask a doctor for help to end their life?
These questions rarely have easy answers. Thoughtful people often disagree, because the facts alone do not settle them.
This guide explains what bioethics is and the principles behind it. Then it walks through 25 of the most debated bioethical issues today, from abortion and cloning to AI and brain implants. Each issue comes with its key ethical questions and a debate question you can use in class.
Bioethics is the study of ethical issues in health care, medicine, research, biotechnology, and the environment.[1] A bioethical issue is a moral question raised by these fields. Many of them appear when new science gives people choices they never had before.
Bioethical Issues Guide:
- What Is Bioethics?
- What Makes an Issue Bioethical?
- Core Principles of Bioethics
- Top Bioethical Issues
- Beginning of Life Issues
- Genetics and Biotechnology Issues
- Research Ethics Issues
- Health Care and End of Life Issues
- Technology and Data Issues
- Far-Future Ideas
- Key Moments in Bioethics History
- How to Analyze a Bioethical Issue
- Bioethics Debate Topics
- Frequently Asked Questions
- Key Takeaways
- Jump to comments
What Is Bioethics?
Bioethics is ethics applied to life and health. Science tells us what we can do. Bioethics asks what we should do.
The field covers health care, medicine, research, biotechnology, and the environment.[1] It draws on biology, medicine, philosophy, law, and religion. People start from different values, so bioethics debates can get heated.
Where the Word Came From
The word joins “bio” meaning life, with “ethics“. The first known use of the term came in 1927, when a German pastor named Fritz Jahr wrote about “Bio-Ethik”[2]
The American cancer researcher Van Rensselaer Potter brought the English word into use in a 1970 article.[3]
Around the same time, scholars at Georgetown University used “bioethics” in a slightly different way. For them, it meant the ethics of medicine, health care, and the life sciences.[4]
What Bioethicists Do
A bioethicist is an expert who studies these moral questions. Many work in hospitals. They help doctors, patients, and families when they disagree about care. This is called clinical ethics consultation.[5]
Bioethicists also serve on ethics committees, write hospital policies, and teach. Others do research or work on health policy.[6]
What Makes an Issue Bioethical?
A bioethical issue is an ethical question that comes up in medicine, health care, biology, biotechnology, public health, or a related life science.[1] Some of these issues are dilemmas, where important values or duties conflict and you cannot honor all of them at once. Others are questions about rights and duties, consent, privacy, risk, or how to write fair rules.
Here is a dilemma. A new cancer drug works, but it costs a fortune. Helping the patient in front of you is good. Spending limited money fairly for everyone is also good. You cannot fully do both.
Not every bioethical issue is that tight a conflict. Who may read a patient’s records, and what a researcher owes a volunteer, are bioethics questions too.
Ethical vs. Bioethical Dilemmas
An ethical dilemma arises when moral requirements or reasons for action conflict and cannot all be satisfied.[7] A step-by-step framework helps you work through one.[8]
A bioethical dilemma is the same kind of conflict inside medicine, health care, or the life sciences. So every bioethical dilemma is an ethical dilemma. But not every ethical dilemma is bioethical. Deciding whether to tell a friend an awkward truth is an ethical dilemma. Deciding how much to tell a frightened patient about a grim diagnosis is a bioethical one.
Core Principles of Bioethics
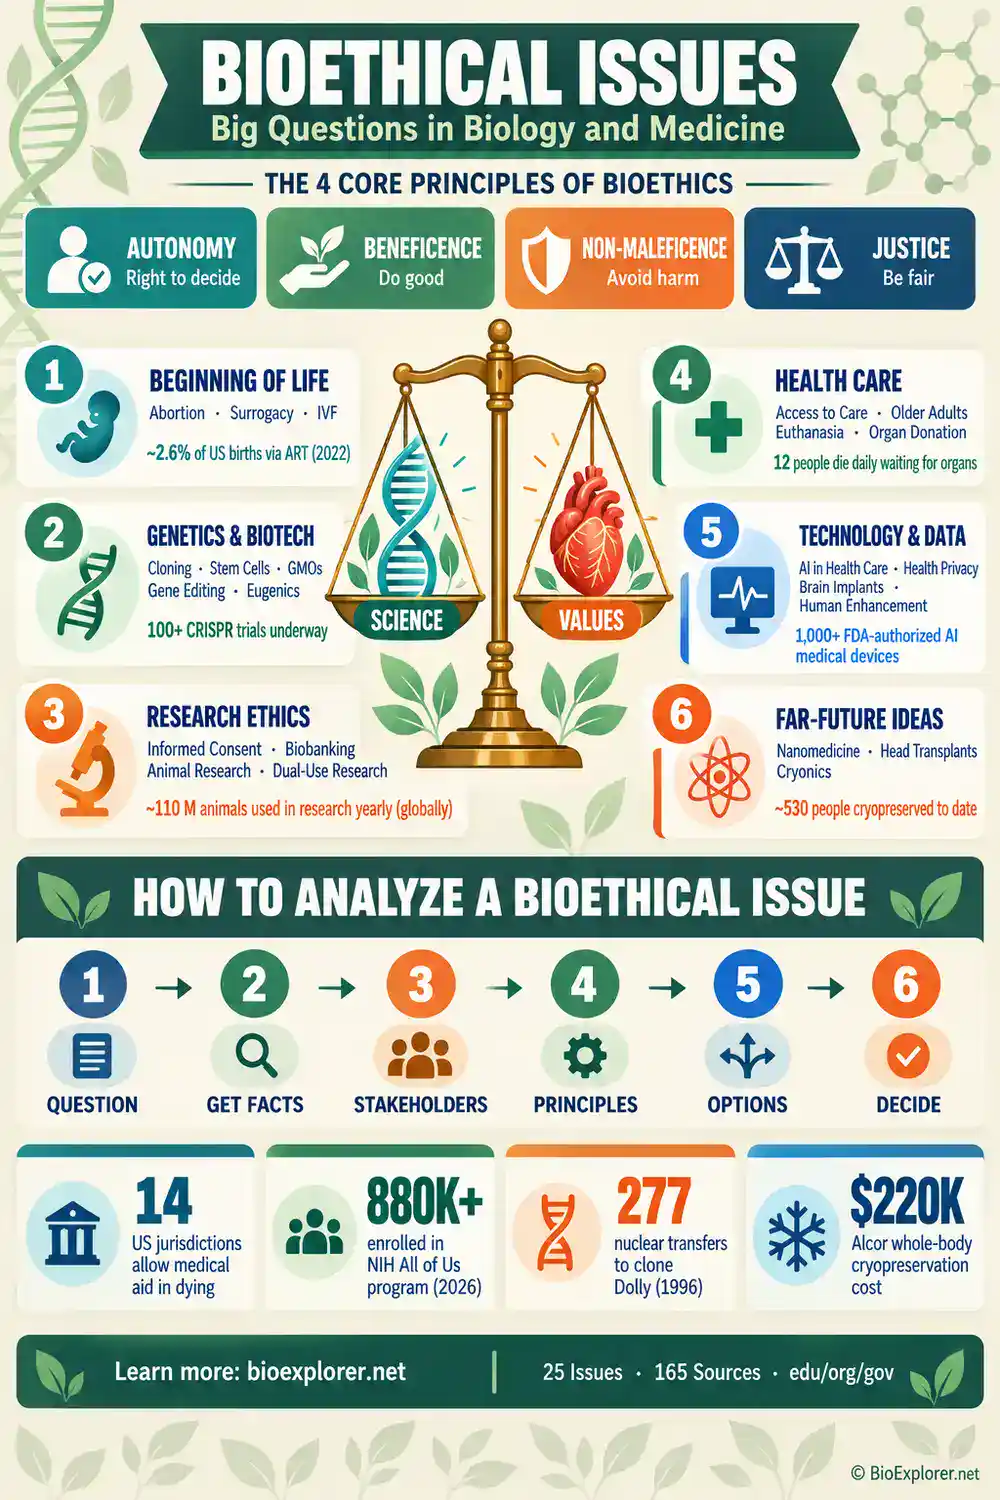
Many bioethics debates come back to four widely taught principles.[9] They give people a shared language, even when they reach different answers.
| Principle | What it means | Example |
|---|---|---|
| Respect for autonomy | People can make informed, voluntary choices about their own care | A patient refuses surgery after hearing the risks |
| Beneficence | Act for the good of the patient, and prevent or remove harm | A doctor recommends a treatment that is likely to help |
| Nonmaleficence | Avoid unnecessary harm, by action or by neglect, and weigh risks against benefits | Researchers stop a trial when side effects become dangerous |
| Justice | Share benefits and burdens fairly | A hospital uses clear, fair rules to decide who gets a scarce ICU bed |
These ideas also shape the rules for research. The 1979 Belmont Report names three basic principles for research on people: respect for persons, beneficence, and justice.[10]
If a question asks about the Belmont Report, give three principles: respect for persons, beneficence, and justice. If it asks about the principles of bioethics in medicine, the usual answer is four: autonomy, beneficence, nonmaleficence, and justice.
Top Bioethical Issues
Here are the 25 bioethical issues covered in this guide. They are grouped into six areas. Select any issue to jump to it.
| No. | Issue | The core question |
|---|---|---|
| 1 | Abortion | Does a fetus have a right to life, and how does that weigh against a pregnant woman’s rights? |
| 2 | Surrogacy | Is it fair to pay a woman to carry a baby for someone else? |
| 3 | IVF and Embryo Screening | Should parents choose which embryos to use? |
| 4 | Cloning | Should we ever copy a human being? |
| 5 | Stem Cell Research | Is it right to destroy embryos to find new treatments? |
| 6 | Eugenics | How do we prevent disease without repeating past abuses? |
| 7 | GMOs | Who controls our food, and what should labels tell us? |
| 8 | Human Gene Editing | Should we change genes that pass to future children? |
| 9 | Newborn Genome Sequencing | Should every baby’s DNA be read at birth? |
| 10 | Precision Medicine | How do we protect privacy and share benefits fairly? |
| 11 | Informed Consent | What must people know before they join a study? |
| 12 | Biobanking | Who controls stored blood, tissue, and DNA? |
| 13 | Animal Research | When, if ever, is it right to experiment on animals? |
| 14 | Dual-Use Research | What if helpful research could also be used to cause harm? |
| 15 | Access to Health Care | Who gets care when there is not enough for everyone? |
| 16 | Care for Older Adults | How do we balance safety and freedom? |
| 17 | Euthanasia and Assisted Dying | Should doctors help patients end their lives? |
| 18 | Organ Donation | How should scarce organs be shared? |
| 19 | AI in Health Care | Can we trust machines with medical decisions? |
| 20 | Health Data Privacy | Who can see, share, or sell your health data? |
| 21 | Brain Implants and Neuroethics | Who should have access to your brain signals? |
| 22 | Human Enhancement | Is it fair to make healthy people better than normal? |
| 23 | Nanomedicine | How safe are tiny particles inside the body? |
| 24 | Head Transplants | Should surgeons try an operation that has never worked? |
| 25 | Cryonics | Is it right to sell the hope of coming back to life? |
Beginning of Life Issues
These issues deal with how life starts and who gets to decide.
1. Abortion

An induced abortion is a medical procedure that ends a pregnancy on purpose. It can be done with medicine or with a procedure. A miscarriage is different. Doctors call it a spontaneous abortion, and it happens on its own before the 20th week of pregnancy.[11]
Abortion is one of the most divided debates in bioethics. Philosophers mostly argue about these questions.[12]
- Does an embryo or fetus have full moral status, like a born person?
- If it does, when does that status begin?
- Even if a fetus has a right to life, does a pregnant woman have the right to control what happens to her own body?
Laws differ widely around the world. In 2022, the US Supreme Court held in Dobbs that the Constitution does not confer a right to abortion. That returned most authority to elected lawmakers, so abortion law now differs sharply from state to state.[13]
When, if ever, should the law limit a person’s choice to end a pregnancy?
2. Surrogacy

In surrogacy, a woman carries a pregnancy for someone else. The people who will raise the child are called the intended parents. There are two types.[14]
- Traditional surrogacy: The surrogate uses her own egg. She is the baby’s genetic mother.
- Gestational surrogacy: The carrier receives an embryo made through IVF. She has no genetic link to the baby.
Gestational surrogacy is now the usual form. Traditional surrogacy is rare in modern clinics.[15]
Key ethical questions:
- Could payment pressure women with little money into carrying a pregnancy?[16]
- Does paid surrogacy treat women’s bodies or babies like products?
- Who are the legal parents if the agreement breaks down?
Laws range from complete bans to legal paid surrogacy.[16] In the United States, each state sets its own rules.[15]
Should paid surrogacy be legal?
3. IVF and Embryo Screening
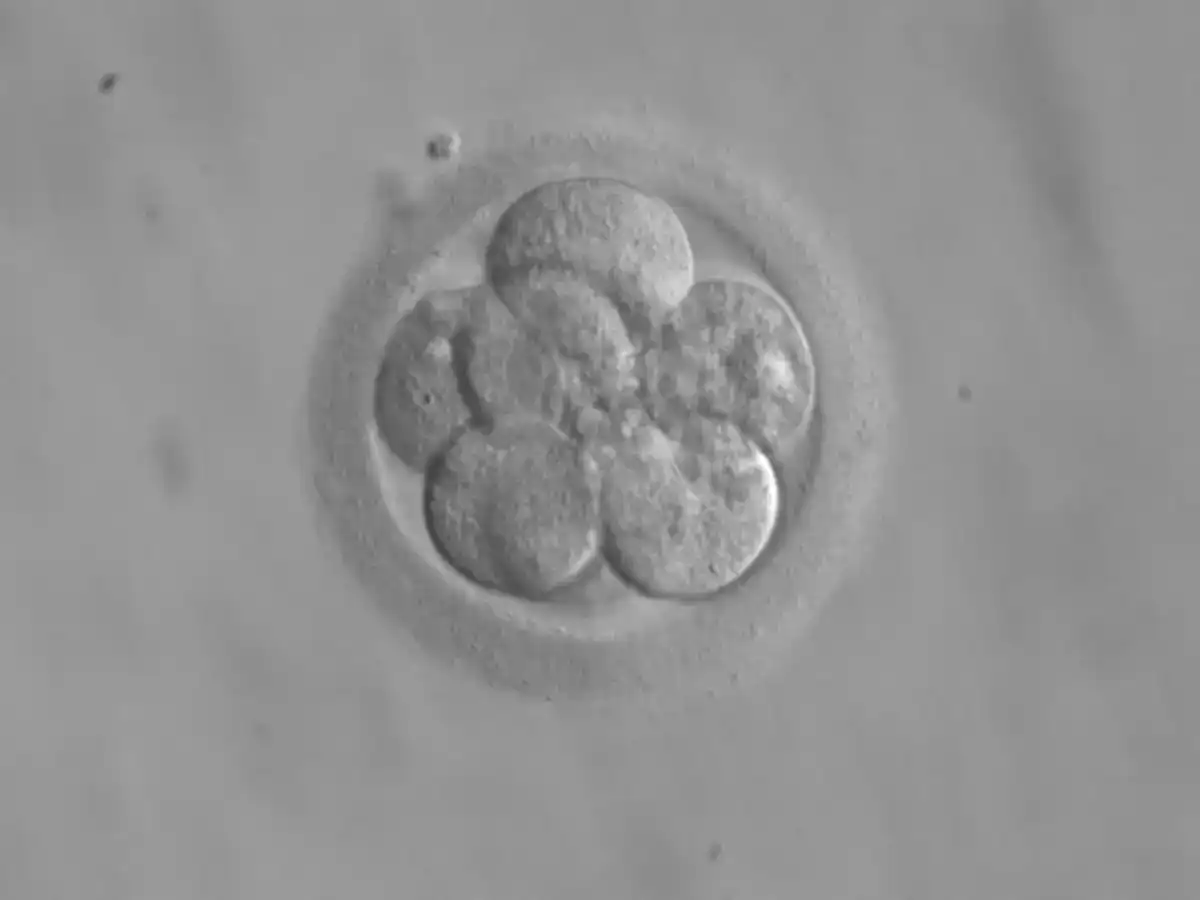
In vitro fertilization (IVF) joins an egg and sperm in a lab dish. The embryo is then placed in the uterus.[17] The first IVF baby, Louise Brown, was born in England in 1978.[18] In 2022, infants conceived using assisted reproductive technology (ART) made up about 2.6 percent of all infants born in the United States.[19]
IVF also lets doctors test embryos before transfer. This is called preimplantation genetic testing (PGT). It can check embryos for specific genetic disorders.[20] Newer tests try to estimate an embryo’s risk for common conditions that involve many genes. The American Society for Reproductive Medicine calls this a nascent and unproven technology. Its ethics committee says it should not be offered clinically yet, and that such testing belongs in research with proper review.[21]
Key ethical questions:
- Could embryo selection slide toward “designer babies” chosen for looks or intelligence?[22]
- Does screening send a negative message about people living with disabilities?[21]
- What should happen to the large number of unused frozen embryos in storage?[23]
- Is it fair that mostly families who can pay get access?
These questions carry real legal weight. In February 2024, the Alabama Supreme Court ruled that frozen embryos count as children under the state’s wrongful death law. Some clinics paused IVF. Alabama then passed a law to protect IVF providers from lawsuits.[24]
A related technique, mitochondrial donation, uses healthy mitochondria from a donor egg. In 2025, UK researchers reported that eight babies had been born this way.[25] In the United States, Congress has barred the FDA from accepting applications for clinical research using this method since 2015.[26] For more, see our guide to the pros and cons of designer babies.
Should parents be allowed to pick embryos for traits that have nothing to do with disease?
Genetics and Biotechnology Issues
Modern biotechnology lets scientists read, copy, and change DNA. These powers raise some of the biggest questions in bioethics.
4. Cloning

Cloning makes a genetic copy of a cell or a whole organism. Scientists move the DNA from a body cell into an egg whose own nucleus has been removed. This is called somatic cell nuclear transfer. There are two main goals.[27]
- Reproductive cloning creates a copy of a whole animal.
- Therapeutic cloning creates embryonic stem cells for research and possible tissue repair. It does not grow spare organs.
Dolly the sheep was born in 1996. She was cloned from the udder cell of an adult sheep. Researchers ran 277 nuclear transfer attempts, and only one produced a live lamb.[27] Cloned animals can also have health problems, such as defects in the liver, brain, and heart. Despite several publicized claims, there is no solid scientific evidence that anyone has cloned a human.[27]
Key ethical questions:
- Is human reproductive cloning ever acceptable, given the high failure rate and health risks?
- Therapeutic cloning destroys early embryos. Is that morally acceptable?
- Would a human clone be treated as a unique person or as a copy of someone else?
Many countries ban human reproductive cloning.[28] To dig deeper, read our guide to the pros and cons of cloning.
Should therapeutic cloning be allowed even if reproductive cloning stays banned?
5. Stem Cell Research

Stem cells can renew themselves and develop into specialized cells. Scientists study three main types.[29]
- Embryonic stem cells come from embryos that are only a few days old.
- Adult stem cells live in tissues such as bone marrow and help repair the body.
- Induced pluripotent stem (iPS) cells are adult cells that have been reprogrammed to act like embryonic stem cells.
The main debate is about embryonic stem cells. Collecting them destroys the embryo. People who believe an embryo has the moral status of a person see this as wrong. Others argue that the chance to treat serious diseases justifies the research.[30]
Scientists made iPS cells from mouse cells in 2006 and from human cells a year later.[31] These cells avoid destroying embryos. They still raise questions, such as whether they could one day be used to make eggs or sperm.[30]
Hype is another problem. The FDA warns about clinics that sell unapproved stem cell treatments. Some of these products have caused blindness, tumors, and infections.[32] Approved options are still limited. Most are blood-forming stem cells from umbilical cord blood.[32] In December 2024, the FDA also approved Ryoncil, the first mesenchymal stromal cell therapy, for a serious complication of bone marrow transplants in children.[33]
Embryo research also has limits. For years, a “14-day rule” served as a widely used ethical limit on growing human embryos in the lab. In some countries it is also written into law. In 2021, the International Society for Stem Cell Research moved research past that point into a category that needs specialized scientific and ethics review.[34] Its current guidelines ask national academies and regulators to lead public conversations first, and any such work still has to follow local law.[35]
Learn more about where stem cells come from and the pros and cons of stem cell research.
Is it right to destroy human embryos if the research could cure serious diseases?
6. Eugenics
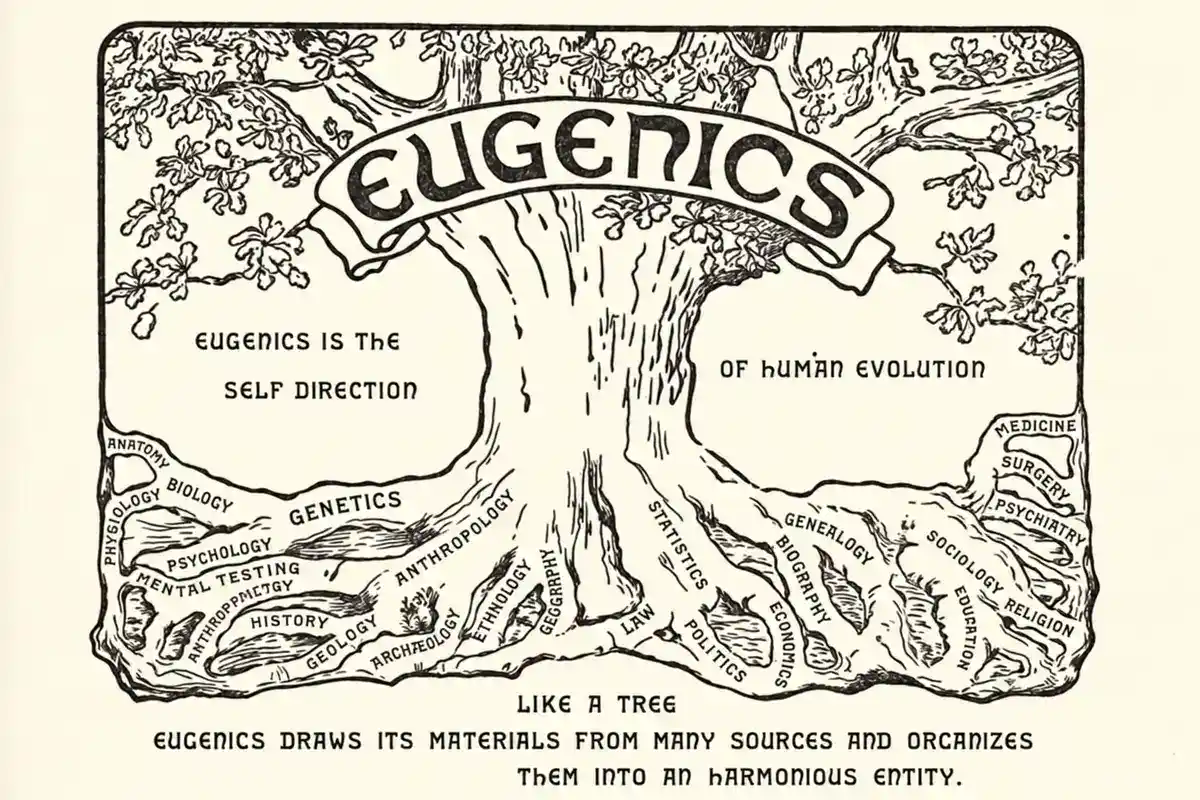
Eugenics is the idea of “improving” the human population by controlling who has children. The British scientist Francis Galton coined the term in 1883.[36]
Eugenics was popular long before Nazi Germany. In the early 1900s, it had wide support in the United States and Britain. US state laws led to the forced sterilization of at least 60,000 people.[36] In 1927, the US Supreme Court upheld forced sterilization in a case called Buck v. Bell.[37]
Nazi Germany took these ideas to horrific extremes. Its 1933 sterilization law was based in part on US practice.[38] Its so-called “euthanasia” program then murdered disabled people. The program was in many ways a rehearsal for the Holocaust.[39]
New genetic tools bring back some old worries. Screening embryos for behavior or intelligence would echo the history of eugenics.[36] Some ethicists warn that polygenic embryo scores raise the specter of eugenics too.[40]
Key ethical questions:
- Where is the line between preventing disease and choosing “better” people?
- Who decides which traits count as undesirable?
- Could social or financial pressure push parents into screening?
Is screening embryos to avoid disease a form of eugenics?
7. Genetically Modified Organisms

A genetically modified organism (GMO) is a plant, animal, or microbe whose DNA has been changed with genetic engineering. GMOs are not new. The first genetically engineered produce, a tomato, went on sale in 1994.[41] Engineered seeds for major field crops arrived in 1996. Today, more than 90 percent of US corn, soybean, and cotton acres are planted with herbicide-tolerant engineered seed.[42]
What about safety? A major 2016 National Academies report found no substantiated evidence that engineered crops on the market are riskier to eat than conventional crops.[43] Much of today’s debate therefore focuses on other questions, including labeling, seed ownership, environmental effects, and animal welfare.
Key ethical questions:
- Labeling: Do shoppers have a right to know what they are buying? Since 2022, US rules require disclosure of bioengineered foods.[44]
- Control of seeds: Companies patent engineered seeds. The US Supreme Court ruled that farmers cannot replant patented seeds without the patent holder’s permission.[45]
- Environment: Some weeds have evolved resistance to glyphosate, the weed killer most engineered crops were built to tolerate.[43]
- Animal welfare: Engineered animals raise welfare concerns.[46] The FDA approved AquAdvantage salmon, an engineered fish, in 2015.[47]
- Gene drives: A gene drive could spread a trait through wild mosquitoes to fight diseases like malaria. In 2016, the National Academies said these organisms were not ready for release.[48]
Read more about the disadvantages of genetically modified foods and the pros and cons of genetic engineering.
Should companies be allowed to patent genetically engineered seeds?
8. Human Gene Editing

CRISPR is a tool that lets scientists change DNA at a chosen spot.[49] Emmanuelle Charpentier and Jennifer Doudna described it in 2012. They won the 2020 Nobel Prize in Chemistry.[50]
The key ethical line falls between two kinds of editing.[49]
- Somatic editing changes body cells in one patient. The changes are not inherited.
- Germline editing changes eggs, sperm, or embryos. The changes can pass to future generations.
Somatic editing is already helping patients. In December 2023, the FDA approved Casgevy for sickle cell disease. It was the first FDA-approved therapy to use CRISPR.[51] In 2025, doctors in Philadelphia treated a baby named KJ with a gene-editing therapy built just for him.[52] NIH called it the first known case of a personalized CRISPR medicine given to a single patient.[53]
Germline editing is far more controversial. In 2018, Chinese scientist He Jiankui announced twin girls whose embryos he had edited. A court later sentenced him to three years in prison.[54] In 2023, organizers of an international summit said heritable human genome editing “remains unacceptable at this time.”[55]
Key ethical questions:
- Future generations cannot consent to changes in their genes.[56]
- Could editing slide from treating disease to enhancing traits?
- Will gene editing only reach the wealthy?[56] Casgevy was listed at $2.2 million per patient.[57]
See our guide to the pros and cons of gene therapy.
Should germline editing ever be allowed to prevent a serious inherited disease?
9. Newborn Genome Sequencing

Newborns in the United States already get a screening test. A nurse makes a small puncture in the baby’s heel and collects a few drops of blood.[58]
Whole genome sequencing reads nearly all of a baby’s DNA. In research studies, it finds more. New York City’s GUARDIAN study found serious conditions in 120 of the first 4,000 babies sequenced. Standard screening had caught only 10 of them.[59] Boston’s BabySeq Project found unexpected disease risks in 11 percent of the babies it sequenced.[60]
Key ethical questions:
- Young children cannot give informed consent.[61] Should parents learn about risks for diseases that only appear in adults?
- Many gene changes have an unclear meaning. Could results cause needless worry?
- Who stores the DNA data, and could it be used to discriminate against the child later?[62]
In the United States, the Genetic Information Nondiscrimination Act (GINA) protects people from genetic discrimination in health insurance and jobs. It does not cover life, disability, or long-term care insurance.[63] Read more about the pros and cons of genetic testing.
Should genome sequencing become a standard test for every newborn?
10. Precision Medicine
Precision medicine tailors prevention and treatment to a person’s genes, environment, and lifestyle.[64] It depends on huge amounts of health data. The NIH All of Us Research Program aims to enroll one million people.[65] By mid-2026, more than 880,000 people had joined.[66]
Key ethical questions:
- Privacy: NHGRI notes that a DNA sample can never be truly anonymized.[67]
- Fairness: In an analysis summarized by NHGRI, about 78 percent of participants in large genomic studies were of European ancestry.[68] Findings may not work as well for groups that were left out.
- Discrimination: Could genetic data affect life insurance or other coverage that GINA does not protect?[63]
- Cost: Will tailored treatments reach everyone, or only people who can pay?
Should companies profit from DNA that research volunteers donate for free?
Research Ethics Issues
Research on people and animals has led to huge medical advances. It has also led to some of the worst abuses in science. These issues are about doing research the right way.
11. Informed Consent

Informed consent means a person agrees to join a study after learning what it involves. The rule grew out of tragedy.
After World War II, Nazi doctors were put on trial for cruel experiments on prisoners. The 1947 Nuremberg Code came out of that trial. Its first rule says: “The voluntary consent of the human subject is absolutely essential.”[69]
The United States had its own scandal. Starting in 1932, the US Public Health Service studied 600 Black men in Tuskegee, Alabama. Of these men, 399 had syphilis. By 1943, penicillin was the treatment of choice for syphilis. Yet the men in the study were not offered it. The study did not end until 1972.[70]
In 1974, Congress passed the National Research Act. It created the national commission that later wrote the Belmont Report.[71] Today, US rules say a consent form must explain:[72]
- The purpose, procedures, and expected length of the study
- The risks and possible benefits
- Other options, such as standard treatment
- How private information will be protected
- That joining is voluntary and you can quit at any time without penalty
An Institutional Review Board (IRB) reviews studies to protect the rights and welfare of the people taking part.[73]
Key ethical questions:
- Can very sick or very poor people give truly free consent?
- When wealthy countries run studies in poorer countries, is there a risk of exploitation?[74]
- How much must people understand before their consent counts as informed?
Should people be paid well to join risky studies, or does money pressure them?
12. Biobanking
A biobank is like a library of biological samples, such as blood, tissue, and DNA, that are stored for research.[75] Many donors give “broad consent.” This lets researchers use their samples in future studies that are not yet planned.[72]
The most famous case is Henrietta Lacks. In 1951, doctors at Johns Hopkins took cells from her cervical tumor without her knowledge or consent. Her “HeLa” cells were the first human cells to be grown steadily for research. They became a vital tool in biomedical science.[76]
Johns Hopkins now says it could have and should have done more to inform and work with the Lacks family.[77] In 2013, NIH and the family reached an agreement on how researchers can access HeLa genome data.[76] In 2023, the Lacks estate settled a lawsuit against a company that sold HeLa cells.[78]
Another case involved the Havasupai Tribe of Arizona. Tribe members gave blood samples starting in 1990. They understood the research was about diabetes. Researchers later used the samples to study schizophrenia, inbreeding, and human migration. In 2010, Arizona State University agreed to pay $700,000 to 41 tribe members and return the samples.[79]
Key ethical questions:
- Who owns your cells once they leave your body? In 1990, the California Supreme Court ruled that a patient had no right to share in profits made from his cells.[80]
- Is broad consent truly informed if no one knows what future studies will do?
- Should donors or their communities share in profits from their samples?
Should people be paid when their cells lead to profitable products?
13. Animal Research

Scientists use animals such as mice and rats to study diseases and test new treatments. NIH says many medical advances came from carefully planned and highly regulated animal studies.[81] But results in animals do not always carry over to people. Alzheimer’s disease and cancer are two examples.[82]
Many rules and guidelines for animal research build on the “3Rs.” William Russell and Rex Burch first defined them in 1959.[83]
- Replacement: Use methods that avoid animals when possible.
- Reduction: Use fewer animals.
- Refinement: Reduce pain and distress.
US rules have gaps and overlaps. The Animal Welfare Act does not cover birds, rats, or mice bred for research.[84] Separate NIH policy covers every live vertebrate animal in research funded or conducted by the Public Health Service.[85]
The field is changing fast. In late 2022, Congress passed the FDA Modernization Act 2.0. It allowed non-animal methods to support new drug testing.[86] In 2025, the FDA announced a plan to phase out animal testing requirements for some drugs. The plan uses tools like computer models and lab-grown organoids.[87] In 2026, the FDA said it had met its first-year goals.[88] NIH also said it would prioritize human-based research methods.[82]
Key ethical questions:
- Do benefits to people justify pain or death for animals?
- Should some animals, such as primates, get extra protection?
- How quickly should non-animal methods replace animal tests?
Should animal testing end once non-animal methods prove reliable?
14. Dual-Use Research

Some research can help or harm, depending on who uses it. NIH calls the riskiest kind “dual-use research of concern.” Its results could be misused to seriously threaten health, crops, animals, or the environment. They could even threaten national security.[89]
The best-known example came in 2011 and 2012. Two research groups reported H5 bird flu viruses, engineered or adapted in the lab, that could spread between ferrets through the air. One study found that only a few mutations were enough to make an H5N1 virus transmissible in ferrets.[90] The goal was to prepare for a possible pandemic. Critics feared the methods could help someone make a dangerous virus. In early 2012, flu researchers announced a voluntary pause on the work.[91]
US policy has shifted many times. In May 2025, an executive order paused federal funding for “dangerous gain-of-function research.”[92] In July 2026, the federal government released a new policy. It bans federal support for this research in the United States and abroad. It also requires independent review for certain other high-risk studies.[93]
New technology adds new worries, and the picture is changing fast. A 2025 National Academies report found that the AI tools of that time could design and redesign toxins. It also found that no available tool could design a new virus, and that physically making AI designs remained a significant barrier.[94]
In August 2026, Stanford researchers reported using an AI model to design new bacteriophages, which are viruses that infect bacteria. They built close to 300 of the designs and found 16 that killed E. coli well.[95]
These bacteriophages infect bacteria rather than human cells. AI design of a new human-infecting virus has not been demonstrated. Even so, that pace is why oversight rules keep being rewritten. In 2024, a group of scientists also warned against ever building “mirror bacteria“. These would be made of molecules with the opposite handedness of normal life.[96]
Key ethical questions:
- Should risky findings be published in full, or kept partly secret?
- Who decides which experiments are too dangerous to do?
- How do we prevent misuse without blocking helpful science?
Should scientists ever make viruses more dangerous in order to study them?
Health Care and End of Life Issues
These issues come up in hospitals, nursing homes, and doctors’ offices every day.
15. Access to Health Care
Health care resources are limited. There are only so many doctors, hospital beds, organs, and dollars. Bioethics asks how to share them fairly. This is the principle of justice at work.
Access is a problem even in wealthy countries. In 2025, 26.7 million people in the United States, or 7.9 percent, had no health insurance for the entire year.[97] New treatments can also cost millions of dollars. Casgevy, the gene-editing therapy for sickle cell disease, was listed at $2.2 million per patient.[57]
The COVID-19 pandemic made these choices painfully real. Some hospitals ran short of ventilators and ICU beds. The National Academies said fairness must come first when sharing scarce life-saving resources.[98] Federal civil rights officials warned that people with disabilities must not be denied care based on stereotypes or judgments about their “worth.”[99]
Key ethical questions:
- Is health care a basic right or a service people buy?
- In a shortage, should care go to the sickest patients, the youngest, or those most likely to survive?
- Should expensive cures be covered for everyone, even if costs strain public budgets?
Should age ever be used to decide who gets a scarce ventilator?
16. Care for Older Adults

The world is aging. By the late 2070s, about 2.2 billion people will be 65 or older. That is projected to be more than the number of children under 18.[100]
Caring for older adults brings hard choices. The biggest is often safety versus freedom. Should an 85-year-old with memory loss keep living alone? Who gets to decide?
Key ethical questions:
- Decision making: Many people with dementia can still express their values and choices in a reliable way.[101] How much weight should their wishes get as the disease advances?
- Planning ahead: Advance directives let people give instructions for their care in case they can no longer speak for themselves.[102]
- Restraints: Nursing homes cannot use physical or chemical restraints to discipline residents or for staff convenience.[103]
- Abuse: About 1 in 10 older adults who live at home experience abuse, neglect, or exploitation.[104]
- Caregivers: Family caregivers carry heavy loads. Nearly 1 in 5 report fair or poor health.[105]
Should adult children be able to move a parent into a care home against the parent’s wishes?
17. Euthanasia and Assisted Dying

These terms often get mixed up, but they mean different things.[106]
- Euthanasia: A doctor directly causes a patient’s death, usually by giving a lethal drug.
- Physician-assisted suicide: A doctor prescribes a lethal drug, and the patient chooses to take it. In the United States, this is often called medical aid in dying.
- Withholding or withdrawing treatment: A patient refuses or stops life support. Many ethicists treat this as separate, because the goal is not to cause death.
Laws vary around the world. The Netherlands, Belgium, Luxembourg, Colombia, Canada, New Zealand, and Spain all allow euthanasia.[107] In the United States, a growing list of states allows medical aid in dying for terminally ill adults. Euthanasia itself remains illegal in every state. Oregon was first, with a law enacted in 1997.[108] More than a dozen US jurisdictions have now authorized the practice.[109]
Two of the newest laws show how long the gap between passing a law and using it can be. Illinois passed its End-of-Life Options for Terminally Ill Patients Act in 2025, and the law took effect on September 12, 2026, after a federal judge declined to block it.[110][111] New York’s governor signed its Medical Aid in Dying Act on February 6, 2026, and that law took effect on August 5, 2026.[112]
Supporters point to patient autonomy and relief from suffering that nothing else can ease. Opponents point to the value of every human life and the risk of pressure on vulnerable people.[106]
The American Medical Association’s Code of Medical Ethics opposes physician-assisted suicide. It calls the practice “fundamentally incompatible with the physician’s role as healer.”[113]
Key ethical questions:
- Is there a moral difference between letting someone die and helping them die?
- Can safeguards protect people who feel like a burden to others?
- Should people with dementia or mental illness ever qualify?
Should medical aid in dying be legal for terminally ill adults?
18. Organ Donation
Organ transplants save lives, but there are not enough organs. In the United States, more than 100,000 people are on the national transplant waiting list. Twelve people die each day while waiting. One donor can save up to eight lives.[114]
So who gets an organ? The US matching system weighs several factors. They include blood type, body size, how sick the patient is, time on the waiting list, and distance between hospitals.[115]
Fame, income, and insurance play no role in transplant priority.[116] Each transplant hospital decides who it will add to its list. A past history of drug or alcohol use does not always rule someone out.[117]
Key ethical questions:
- Consent: The United States uses an opt-in system, so people must choose to be donors. Some countries count everyone as a donor unless they opt out.[118] Which system is more ethical?
- Trafficking: Organs are sometimes taken without valid consent or sold for money. The Declaration of Istanbul condemns organ trafficking and transplant tourism.[119]
- Living donors: How much risk should a healthy person accept to help someone else?
What about pig organs? Scientists are testing gene-edited pig organs to ease the shortage. This is called xenotransplantation. In 2022, a patient at the University of Maryland lived for two months after receiving a pig heart.[120] A latent pig virus, porcine cytomegalovirus, was later detected in the heart.[121] Its exact role is uncertain.
Later analysis suggested that the virus may have contributed to inflammation in the organ and to the patient’s decline.[122] In 2025, another patient lived 271 days with a pig kidney without needing dialysis. He later received a human kidney.[123] In late 2025, NYU Langone Health performed the first transplant in a clinical trial of gene-edited pig kidneys.[124]
Xenotransplants raise new concerns. These include animal welfare, the risk of animal viruses spreading to people, and consent from very sick patients. Recipients may need lifelong monitoring, which limits their right to leave the study.[125] Read more about the pros and cons of organ donation.
Should the United States switch to an opt-out organ donation system?
Technology and Data Issues
Digital tools and new devices are changing medicine quickly. Laws and ethical guidelines are working to keep up.
19. AI in Health Care

Artificial intelligence (AI) already helps read medical scans and flag patients at risk. The FDA keeps a public list of AI-enabled medical devices authorized for sale in the United States.[126] As of 2025, more than three out of four were for radiology, or medical imaging.[127]
AI can make care faster. But it can also fail in ways that are hard to see. A well-known 2019 study found that a widely used health algorithm was racially biased. It predicted health care costs instead of illness. Less money had been spent on Black patients, so Black patients with the same risk score were actually sicker than White patients.[128]
Key ethical questions:
- Bias: Will AI trained on unequal data make unequal decisions?
- Transparency: Should patients and doctors know how an AI tool works and how well it performs?[129]
- Accountability: Who is responsible when AI makes a mistake?
- Human oversight: The American Medical Association uses the term “augmented intelligence.” It stresses that AI should support human judgment, not replace it.[130]
Should patients be told every time AI helps make a decision about their care?
20. Health Data Privacy
Your health data lives in many places. It sits in medical records, fitness trackers, health apps, and DNA test kits. Not all of it has the same protection.
In the United States, HIPAA protects health data held by health plans, most health care providers, and their business associates.[131] It generally does not protect health information on your personal phone or tablet.[132]
In 2024, the Federal Trade Commission updated its Health Breach Notification Rule. Many health apps and connected devices that fall outside HIPAA must now tell users, and the FTC, after a breach of identifiable health data.[133]
A major test came in 2025. The DNA testing company 23andMe filed for bankruptcy. California’s attorney general reminded customers that they could ask the company to delete their genetic data.[134] A judge later approved the company’s sale to a nonprofit led by its co-founder.[135]
Key ethical questions:
- Who should control your health data: you, your doctor, or the company that collects it?
- Should companies be allowed to sell or share health data for profit?
- Can “anonymous” genetic data stay anonymous?[67]
Should health apps follow the same privacy rules as hospitals?
21. Brain Implants and Neuroethics
Neuroethics is a field that studies the ethical, legal, and social questions raised by brain science.[136]
Brain-computer interfaces are one reason the field is growing fast. These devices read signals from the brain and turn them into actions. In 2024, UC Davis Health reported on a brain implant for a man with ALS. It let him “speak” through a computer with up to 97 percent accuracy.[137] That same year, the company Neuralink announced its first human implant.[138]
Key ethical questions:
- Mental privacy: Brain data could reveal very personal information. NIH neuroethics principles call for protecting the privacy of neural data.[139] In 2024, Colorado added neural data to the sensitive data protected by state privacy law.[140] California and Montana passed similar protections.[141][142]
- Identity: If a device changes mood or behavior, who is really in control?
- Consent: People with paralysis may feel they have no other option. Can they freely weigh the risks of an experimental implant?
Should brain data get stronger legal protection than other health data?
22. Human Enhancement

Most medicine aims to treat disease. Enhancement aims to improve normal abilities. In 2003, the President’s Council on Bioethics described enhancement as using biotechnology to boost the “native capacities” of a healthy body and mind.[143] In real life, the line between therapy and enhancement is often blurry.
Powered exoskeletons show both sides. In 2014, the FDA authorized the ReWalk exoskeleton. It helps some people with spinal cord injuries walk with a trained companion.[144] Other exoskeletons help workers lift heavy loads. But many are designed around male bodies and may fit women poorly.[145]
Enhancement shows up in other places too. Some healthy students take prescription stimulants to boost their studying before exams.[146] In sports, gene doping is banned. It means using genes or cells to boost athletic performance rather than to treat illness.[147]
Key ethical questions:
- Is it fair if only wealthy people can afford enhancements?
- Will people feel pressure to enhance just to keep up at school or work?
- If enhancement becomes normal, how will we treat people who choose not to enhance?
Should healthy students be allowed to use “smart drugs” to study?
23. Nanomedicine
Nanomedicine uses nanotechnology to prevent, diagnose, and treat disease.[148] The nanoscale runs from about 1 to 100 nanometers. A nanometer is one billionth of a meter.[149]
Nanomedicine is already in use. Doxil, one of the best-known nano-based cancer drugs, was approved by the FDA in 1995.[150] The mRNA COVID-19 vaccines use lipid nanoparticles, tiny “bubbles of fat” that carry mRNA into cells.[151]
Key ethical questions:
- Safety: Nanoscale materials can behave differently from larger forms of the same material. Safety can depend on composition, size, shape, surface properties, dose, and route of exposure, so the FDA reviews these products case by case.[152] Research on possible risks continues.[153]
- Environment: What happens when nanomaterials end up in water and soil?
- Consent: How do you explain risks that are not yet fully known?
- Access: Will advanced treatments reach patients who cannot afford them?
Should nanomedicines go through extra safety testing before approval?
Far-Future Ideas
These two ideas get a lot of attention online. Neither has ever worked in a human. They are still worth studying, because they test our ideas about identity, death, and false hope.
24. Head Transplants
A head transplant would attach a person’s head to a donor’s body. It has never been done on a living human.
In 1970, surgeon Robert White transplanted a monkey’s head onto another monkey’s body. The monkey could not move its new body. Sources report that it lived eight or nine days.[154][155]
In 2017, surgeons Sergio Canavero and Xiaoping Ren described a practice procedure on human cadavers. Other experts said many more steps were needed before anyone could attempt it on a living patient.[156]
Key ethical questions:
- Can someone give true informed consent to surgery with so little evidence behind it?[155]
- Would the person who wakes up still feel like the same person?
- One donor body could provide organs to save several lives. Is it fair to use it for one risky operation?[157]
Should any country allow a human head transplant trial?
25. Cryonics

Cryonics means preserving a body or brain at very low temperatures after death, in the hope that future science can bring the person back. In the United States, a person must first be declared legally dead.[158] No one has ever been revived.
Cryonics is not the same as cryopreservation in medicine. Freezing sperm, eggs, and embryos is a proven technique. Frozen embryos can be thawed and used to start a pregnancy.[159] The Society for Cryobiology is a scientific group for researchers who study life at low temperatures. It calls cryonics “speculation or hope, not science.”[160]
Key ethical questions:
- Is it fair to sell costly services based on an unproven hope?[161] Prices vary by provider and by type of preservation. One long-running US provider currently lists $220,000 for whole-body preservation and $80,000 for neuropreservation, which covers the brain only.[162]
- How can anyone give informed consent to a process that has never worked?
- If revival ever became possible, what rights would a revived person have?
Should companies be allowed to sell cryonics without evidence that revival is possible?
Key Moments in Bioethics History
Many of today’s bioethics rules came from real events. This timeline shows the milestones students most often need to know.
| Year | What happened |
|---|---|
| 1932 | The Tuskegee syphilis study begins. It runs until 1972.[70] |
| 1947 | The Nuremberg Code says voluntary consent is essential in research.[69] |
| 1951 | Cells are taken from Henrietta Lacks without her consent.[76] |
| 1970 | Van Rensselaer Potter brings the word “bioethics” into English.[3] |
| 1974 | Congress passes the National Research Act.[71] |
| 1978 | Louise Brown, the first IVF baby, is born.[18] |
| 1979 | The Belmont Report sets out principles for research on people.[10] |
| 1996 | Dolly the sheep is born.[163] |
| 1998 | Scientists isolate the first human embryonic stem cell lines.[164] |
| 2003 | The Human Genome Project is completed.[165] |
| 2006 | Scientists make the first iPS cells from mouse cells. Human iPS cells follow in 2007.[31] |
| 2012 | Charpentier and Doudna describe CRISPR gene editing.[50] |
| 2018 | He Jiankui announces the first gene-edited babies.[54] |
| 2022 | A living patient receives a gene-edited pig heart.[120] |
| 2023 | The FDA approves Casgevy, its first CRISPR-based therapy.[51] |
| 2025 | A baby receives the first personalized CRISPR therapy.[53] |
How to Analyze a Bioethical Issue
Teachers often ask students to choose a controversial bioethical issue and analyze its ethical concerns. A decision-making framework makes this easier.[8] Try these six steps.
- Turn the issue into a question: For example: “Should parents be allowed to edit an embryo’s genes to prevent disease?”
- Get the facts: What does the science say? What is possible today, and what is not?
- List the stakeholders: Name everyone affected, such as patients, families, doctors, future children, and society.
- Apply the principles: Ask how each option respects autonomy, does good, avoids harm, and treats people fairly.
- Weigh the options: Lay out the strongest arguments on each side. Look for middle-ground solutions.
- Decide and defend: Choose the option you think is best. Explain why, and admit its weak points.
Issue: Should genome sequencing be offered for every newborn?
Facts: In one large study, it found serious conditions that standard screening missed.[59]
Stakeholders: babies, parents, doctors, and insurers.
Principles: Beneficence supports finding treatable diseases early. Autonomy is tricky, because babies cannot consent. Justice asks whether all families would get equal access.
One possible decision: Offer sequencing to parents who want it, and report only conditions that can be treated in childhood.
Bioethics Debate Topics
Need a topic for a debate, essay, or research paper? Start with one of these questions.
| Topic | Question to explore |
|---|---|
| Gene editing | Should germline editing be allowed to prevent serious inherited diseases? |
| Embryo screening | Should parents be able to choose embryos for non-medical traits? |
| Organ donation | Should the United States adopt an opt-out donation system? |
| Assisted dying | Should medical aid in dying be legal for terminally ill adults? |
| AI in medicine | Who should be responsible when a medical AI makes a mistake? |
| Animal research | Should animal testing end once non-animal methods prove reliable? |
| Health data | Should DNA testing companies be allowed to share customer data? |
| Access to care | Should expensive gene therapies be covered for everyone? |
| Human enhancement | Should “smart drugs” be banned for healthy students? |
| Biobanking | Should donors share in the profits from their cells? |
| Dual-use research | Should risky virus research be published in full? |
| Surrogacy | Should paid surrogacy be legal? |
Frequently Asked Questions
Bioethical issues are moral questions raised by biology, medicine, health care, and the life sciences. Many come from new technology. Common examples include abortion, cloning, stem cell research, gene editing, euthanasia, organ donation, and the use of AI in medicine.
Well-known examples include abortion, surrogacy, IVF and embryo screening, cloning, and stem cell research. Others are eugenics, GMOs, and human gene editing. In research and health care, examples include informed consent, animal research, euthanasia, organ donation, AI in health care, and health data privacy.
There is no single answer. Abortion, euthanasia, and heritable human gene editing are among the most debated. They touch deeply held beliefs about life, death, and future generations.
It is called bioethics. Bioethics studies ethical issues in health care, medicine, research, biotechnology, and the environment.
Look for a question about life, health, or the life sciences that turns on values, not just facts. Deciding whether to edit an embryo’s genes, or who gets a scarce organ, are bioethical issues. The boiling point of water is a science fact, not a bioethical issue.
The four core principles are respect for autonomy, beneficence, nonmaleficence, and justice. The Belmont Report on research ethics lists three: respect for persons, beneficence, and justice.
An ethical dilemma arises when moral duties or reasons conflict and cannot all be satisfied. A bioethical dilemma is the same kind of conflict in medicine, health care, or the life sciences.
A bioethicist studies moral questions in medicine and the life sciences. Many advise doctors, patients, and families in hospitals. Others serve on ethics committees, write policies, teach, do research, or work on health policy.
Bioethics helps protect patients and research volunteers. It helps society decide how to use powerful new technologies fairly and safely. Many of its rules grew out of past abuses, such as the Tuskegee syphilis study.
Two clear examples are human gene editing and animal research. Germline gene editing affects future generations who cannot consent. Animal research raises the question of whether benefits to people justify harm to animals.
Common examples include informed consent, access to care, and sharing scarce resources like ICU beds and organs. Others are end of life decisions, care for older adults with dementia, patient privacy, and the use of AI in diagnosis.
Key issues include human gene editing, cloning, and embryonic stem cell research. Others are GMO labeling, seed patents, gene drives, and the very high cost of new gene therapies.
Key Takeaways
- Bioethics studies moral questions in health care, medicine, research, biotechnology, and the environment.
- An issue is bioethical when it raises an ethical question in medicine, health care, or the life sciences. Some of these issues are dilemmas, where good values conflict.
- Four core principles guide many debates: autonomy, beneficence, nonmaleficence, and justice.
- Modern research rules grew out of abuses such as Nazi medical experiments and the Tuskegee study.
- Beginning of life issues include abortion, surrogacy, and embryo screening.
- Cloning, stem cells, GMOs, and CRISPR raise questions about consent, safety, and fairness.
- Health care issues often come down to who gets scarce care and who gets to decide.
- AI, health data, and brain implants are fast-growing areas where laws are still catching up.
- Strong bioethical reasoning weighs the facts, the stakeholders, and the principles before reaching a decision.
Cite this page
BioExplorer. (2026, September 17). Bioethical Issues: 25 Controversial Examples Explained. https://www.bioexplorer.net/bioethical-issues.html/



One Comment